




The global shortage of mental health professionals is well documented — the World Health Organization estimates that close to one billion people live with a mental health disorder, yet the majority of countries allocate less than 2% of their health budgets to mental health services. Behind this systemic gap lies a quieter but equally significant problem: the shortage is not only of practitioners, but of adequately trained ones. Psychiatric consultation is among the most technically demanding and emotionally complex skills in clinical medicine, yet the opportunities to practice it safely and repeatedly during training remain severely limited.
Unlike physical examination skills, psychiatric interviewing cannot be practiced on a mannequin. Standardized patients can simulate depression or anxiety to a degree, but human actors cannot sustain consistent, clinically accurate portrayals of psychosis, dissociation, or personality disorders across dozens of repetitive training sessions without fatigue or variation. Here’s when technology can enter the game.
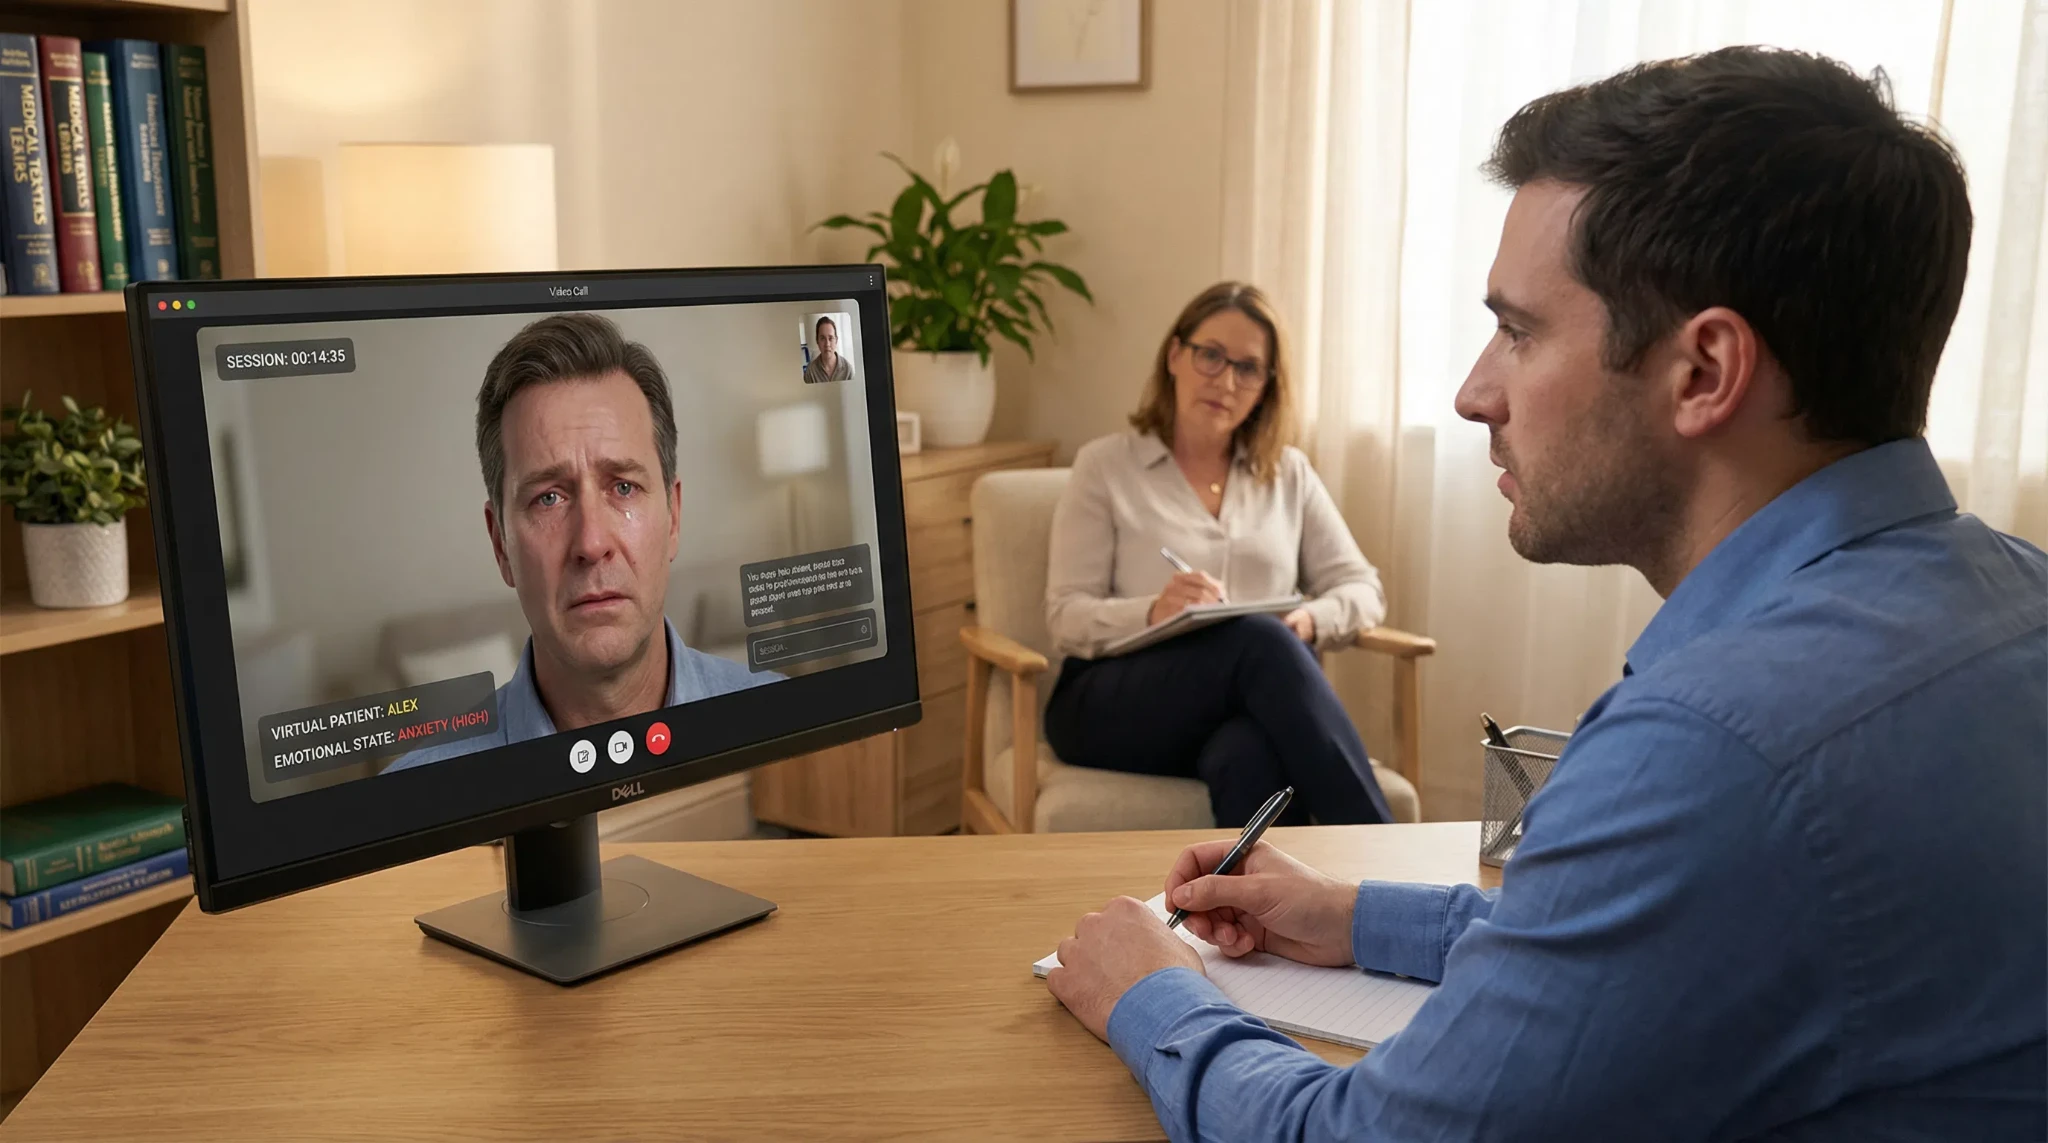
The growing adoption of AI avatars for education — and specifically AI-powered virtual psychiatric patients — is beginning to address this gap in a way that no previous simulation method has been able to match. That’s why medical schools, psychiatry residency programs, and nursing faculties are increasingly exploring virtual patient platforms as a core component of mental health curriculum delivery.
What Is an AI Virtual Psychiatric Patient?
An AI virtual psychiatric patient is a digitally rendered human avatar configured to simulate a specific mental health condition during a clinical consultation. The avatar is built on a combination of large language model (LLM) technology, neural voice synthesis, and photorealistic 3D rendering, enabling it to present symptoms, respond to clinical questioning, and behave in ways consistent with a defined psychiatric profile.
In other words, a trainee psychiatrist or mental health nurse can sit across from a virtual patient presenting with auditory hallucinations, express suicidal ideation, display the pressured speech patterns of a manic episode, or exhibit the emotional blunting characteristic of schizophrenia — and practice their clinical response in a safe, repeatable, and consequence-free environment. The avatar does not tire, does not break character, and does not require scheduling, compensation, or emotional debriefing after a session.
Given this capability, AI virtual patients are not simply a convenience tool. They represent a qualitative shift in how psychiatric competency can be developed — one that allows training volume, scenario diversity, and performance measurement to scale in ways that human-based simulation cannot.
When Does It Make Sense to Use AI Virtual Psychiatric Patients?
You should attentively analyze whether this technology fits the specific learning objectives of your program before integrating it into the curriculum. The format delivers the strongest outcomes in defined training contexts.
AI virtual psychiatric patients are particularly well-suited for:
- Psychiatric history-taking practice — enabling trainees to develop structured interview skills across a wide range of presentations without consuming clinical placement time.
- Suicide risk assessment training — allowing students to practice sensitive, high-stakes conversations in a safe environment where errors carry no real-world consequences.
- Mental state examination (MSE) skill development — presenting consistent, reproducible symptom profiles for trainees to observe, assess, and document.
- Communication training for difficult presentations — including patients who are hostile, paranoid, dissociative, or experiencing acute psychotic episodes.
- Cultural competency development — configuring avatars to reflect different cultural backgrounds, belief systems, and communication styles relevant to psychiatric presentation.
- Formative assessment and remediation — identifying trainees who need additional support before they enter live clinical environments.
Apart from this, AI virtual patients are highly effective for continuous professional development among qualified practitioners who need to maintain or expand their psychiatric interview skills outside of formal training programs.
Key Features of a Reliable AI Psychiatric Simulation Platform
What is also important here is that not all virtual patient platforms are built with the clinical depth that psychiatric training demands. When evaluating solutions, pay attention to the following criteria.
What a Reliable AI Psychiatric Patient Platform Should Have:
- Clinically validated symptom profiles The avatar’s behavioral and verbal outputs should be designed in consultation with practicing psychiatrists and mapped to established diagnostic frameworks such as DSM-5 or ICD-11. This functionality is designed to ensure that trainees are practicing against presentations that reflect real-world clinical encounters, not simplified approximations.
- Dynamic conversational responsiveness A reliable system will enable the avatar to respond to unexpected trainee inputs without breaking clinical consistency. Pay attention to whether the platform can handle non-linear interviews — trainees rarely follow a textbook sequence, and the avatar must be capable of managing that variation without generating clinically inaccurate responses.
- Emotional and behavioral modulation The most highly demanded options are platforms where the avatar’s affect, speech pattern, and behavioral presentation shift dynamically in response to the trainee’s approach. If a trainee de-escalates effectively, the avatar should respond accordingly. If rapport is poorly established, the avatar’s engagement should reflect that outcome.
- Detailed performance analytics Solutions are built based on interaction logging architecture that captures including, but not limited to: question sequencing, empathic language use, risk identification accuracy, and time-to-key-clinical-finding. These mechanics boost the educational value of each session and allow faculty to identify patterns across cohorts.
- Scenario library depth and customization The most widely used options offer both a curated library of pre-built psychiatric cases and the ability to create institution-specific scenarios aligned with local curriculum requirements. You should look for platforms that cover the full range of common and complex presentations — from generalized anxiety to first-episode psychosis.
- Integration with existing learning management systems Typical integrations include connections to Moodle, Canvas, and institutional LMS platforms, enabling session data and performance reports to feed directly into existing academic workflows without requiring manual data transfer.
How to Integrate AI Virtual Psychiatric Patients Into a Mental Health Curriculum
Deploying this technology effectively requires structured planning across content alignment, faculty preparation, and student onboarding.
- Map simulation scenarios to learning outcomes. Identify which psychiatric competencies are currently underserved by existing training methods — history-taking, risk assessment, MSE documentation — and select or configure avatar scenarios that directly address those gaps.
- Involve clinical faculty in scenario validation. It will be helpful to have practicing psychiatrists review avatar symptom profiles and conversational logic before deployment. Faculty endorsement of clinical accuracy is essential for student confidence in the simulation format.
- Introduce the platform in a low-stakes context first. We recommend beginning with a supervised group session where students can observe a demonstration interaction before attempting solo practice. This reduces initial resistance and establishes shared expectations for the format.
- Set clear session objectives for each avatar encounter. If you want trainees to extract maximum learning value from each simulation, you need to frame each session around specific competencies rather than open-ended exploration.
- Use analytics data to inform supervision priorities. Performance reports should be reviewed by faculty to identify trainees who are struggling with specific skills — risk assessment accuracy, empathic communication, or symptom recognition — so that supervision time can be allocated where it is most needed.
- Combine virtual patient practice with reflective debriefing. From a financial perspective, simulation sessions deliver significantly more value when followed by structured reflection. We recommend scheduling dedicated debrief time after each avatar encounter to consolidate learning and address clinical reasoning gaps.
Conclusion
Psychiatric consultation training has long been constrained by the availability of suitable practice opportunities — a limitation that carries real consequences for the quality of mental health care delivered by newly qualified practitioners. AI virtual psychiatric patients offer a scalable, clinically rigorous alternative that enables trainees to build competency across the full spectrum of psychiatric presentations, without placing real patients or human actors under pressure.
The integration of AI virtual patients into mental health training curricula allows institutions to close the practice gap that standardized methods cannot address — delivering consistent, measurable, and repeatable simulation experiences that directly translate into stronger clinical performance. Thanks to this technology, the next generation of mental health practitioners can enter clinical environments better prepared, more confident, and more capable of delivering the quality of care that patients need.




